Admissions & flow
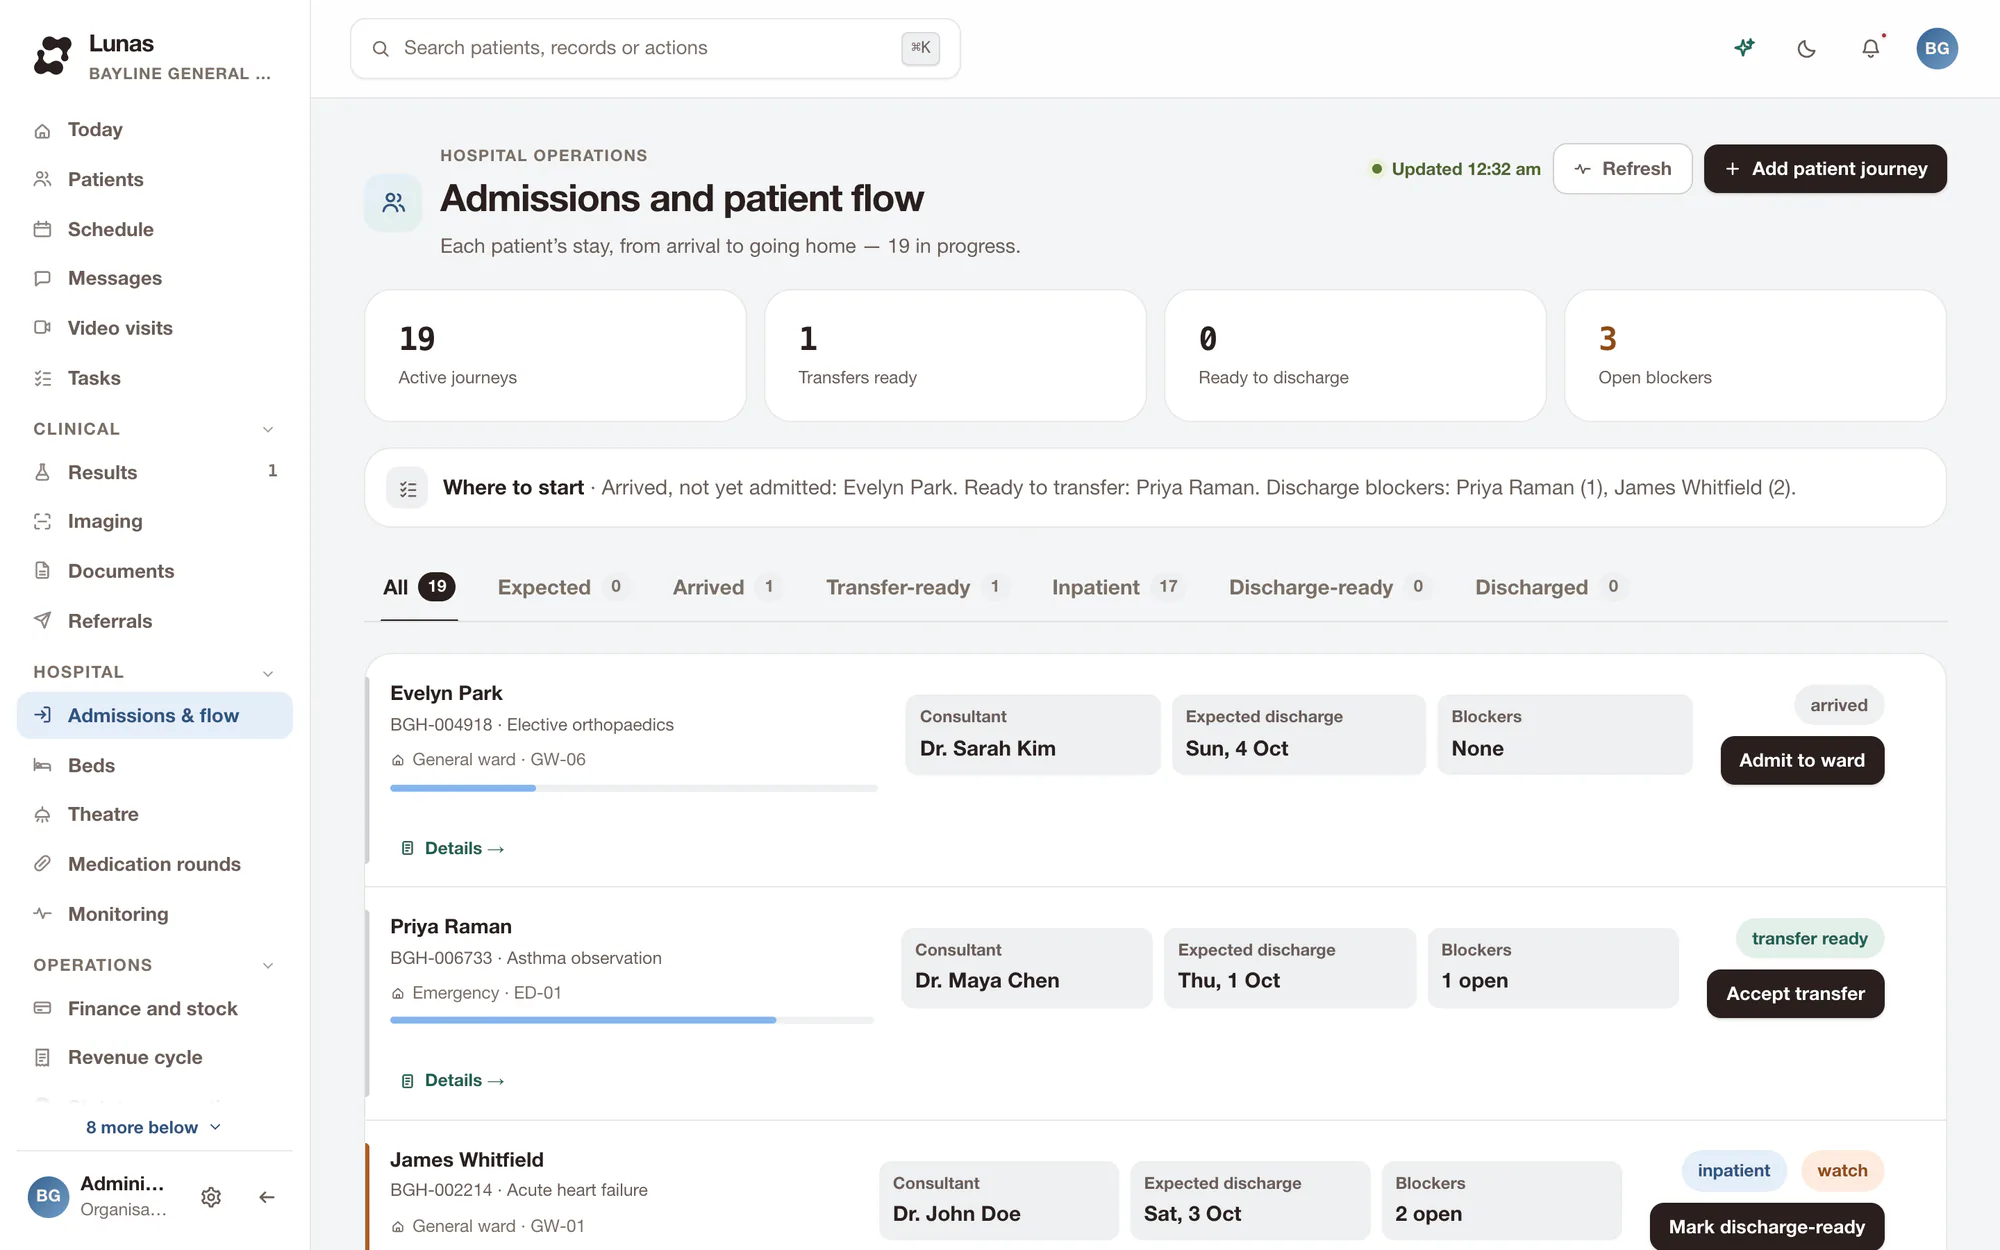
Every patient journey from expected arrival through to completed discharge, with the blockers that are holding each one up.
Six statesexpected → arrived → transfer-ready → inpatient → discharge-ready → dischargedAdmissions and flow, beds, theatre, medication rounds, rostering, monitoring, statutory reporting and revenue — running on the same patient records your clinicians already work in, not a second system bolted alongside.
Every module is enabled per organisation. A hospital opens a command centre; a single clinic never sees any of it.
The command centre, the bed board, the drug round checked by barcode, theatre and the reports. Narrated, with captions.
Each module writes to the same organisation-scoped records, so the command centre reads one live picture rather than reconciling eight of them.
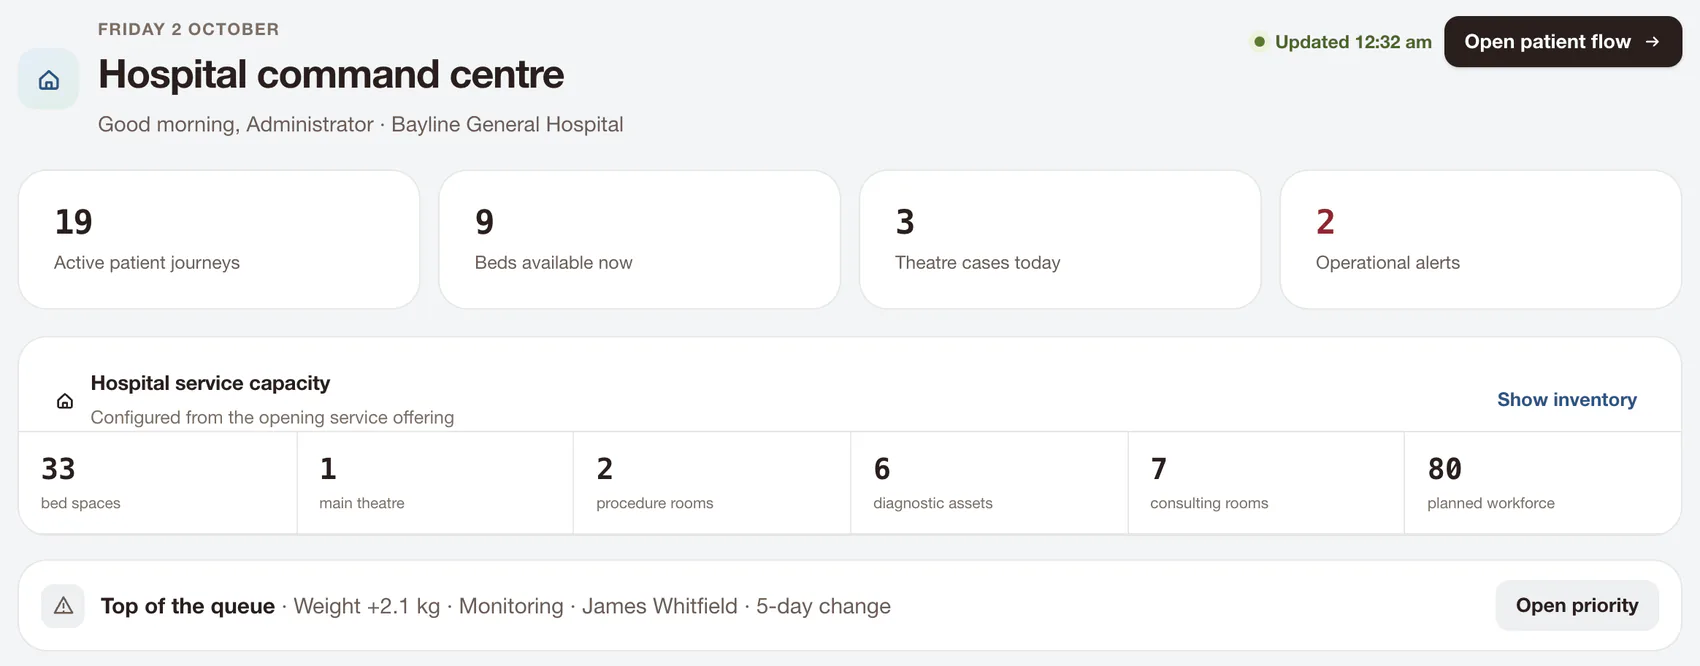
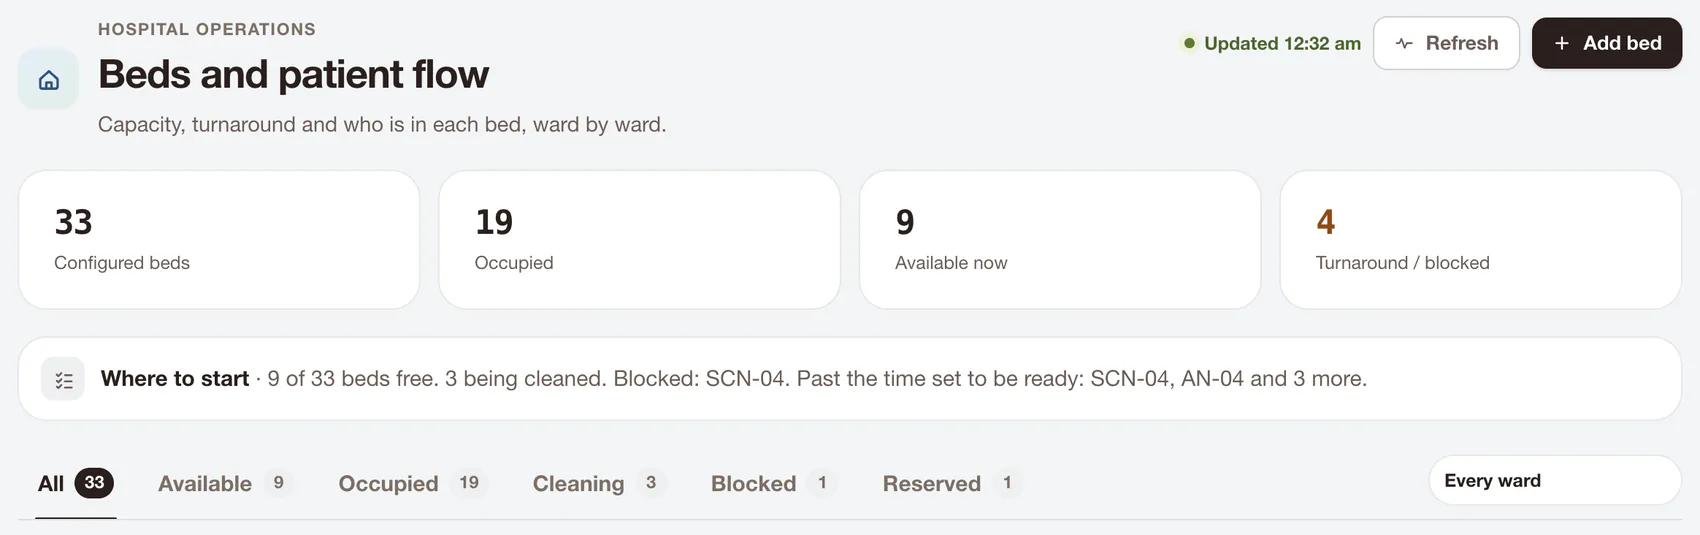
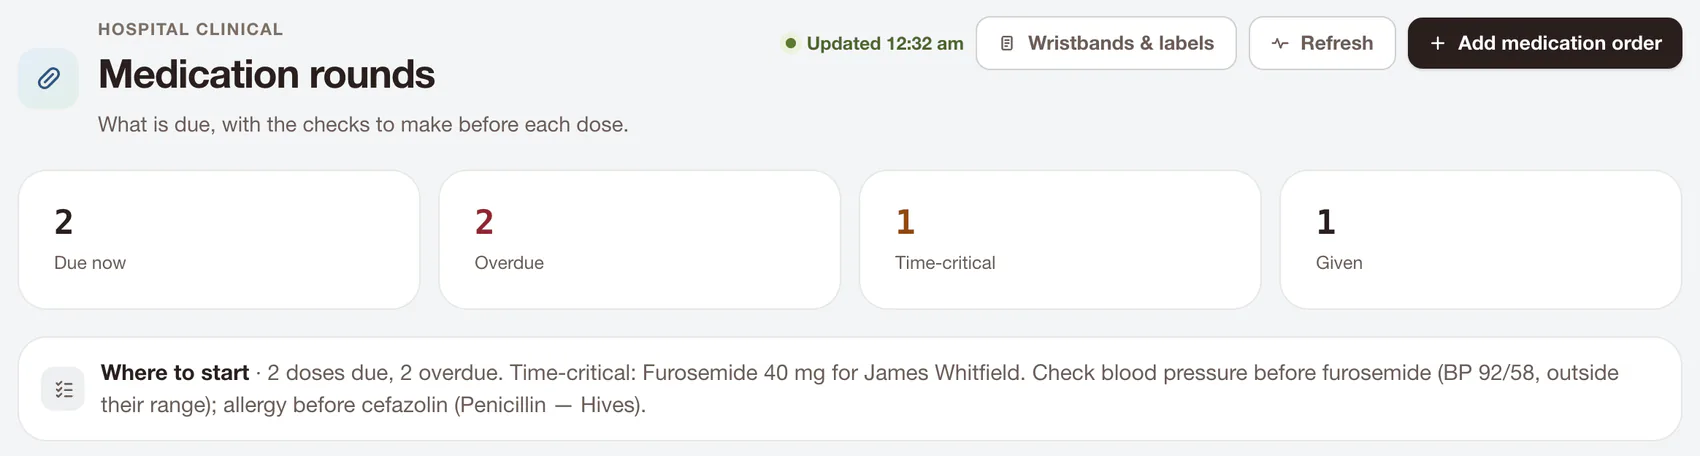
Product screens from the Lunas demo, with invented patients.
Nothing here is a separate product. Each module reads and writes the same patients, staff and audit trail, and each is switched on per organisation and per role.
Every patient journey from expected arrival through to completed discharge, with the blockers that are holding each one up.
Six statesexpected → arrived → transfer-ready → inpatient → discharge-ready → dischargedLive bed state across wards and service lines, so capacity conversations start from what is actually free right now.
Cleaning turnaroundavailable, reserved, occupied, cleaning and blocked, each with an ownerCase readiness, safety checks and progression through the list — with a running note any member of the team can write during the procedure.
Notes are appendednever overwritten, attributed to the author, and written to the audit trailThe administration round as a worklist: what is due, for whom, by which route, and what was given or deliberately held.
Held is a first-class outcomea hold records who decided and why, rather than a blankCoverage planned week by week or month by month, with the credential and capability checks that make an assignment safe.
Moves are re-validateda shift cannot be moved into approved leave or an overlapping shiftDevice and observation alerts triaged into one queue, with acknowledgement and escalation recorded against each one.
Escalation is trackednormal → alert → acknowledged → escalated → resolvedCollections drafted, validated, approved and submitted, so the reporting obligation is a workflow rather than a spreadsheet.
Validation before approvala collection cannot be submitted until its validation has passedCoding, exceptions, claim submission and payment reconciliation, joined to the clinical record the activity came from.
Exceptions surface firstthe queue leads with what is blocking payment, not what is already cleanThe rest work the same way: a worklist, a safe transition, and a record of who did what.
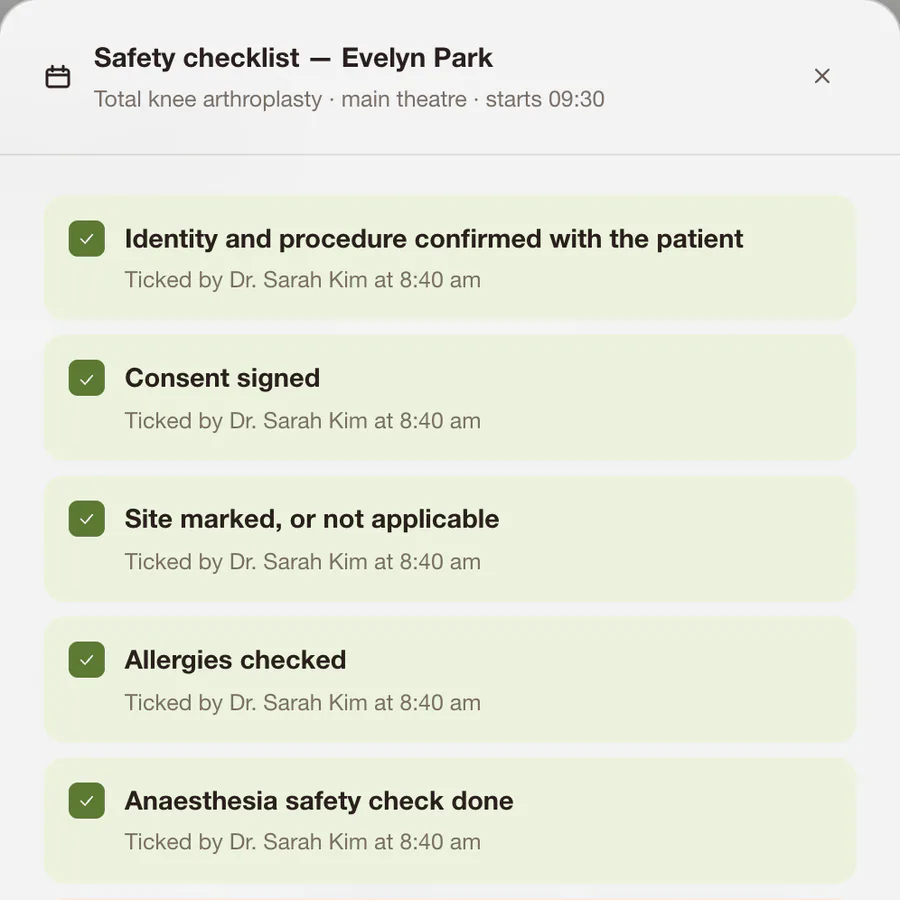
A case carries the checklist, the surgeon and anaesthetist, the planned start and its progression through the list. During the procedure, anyone in the room can write to it.
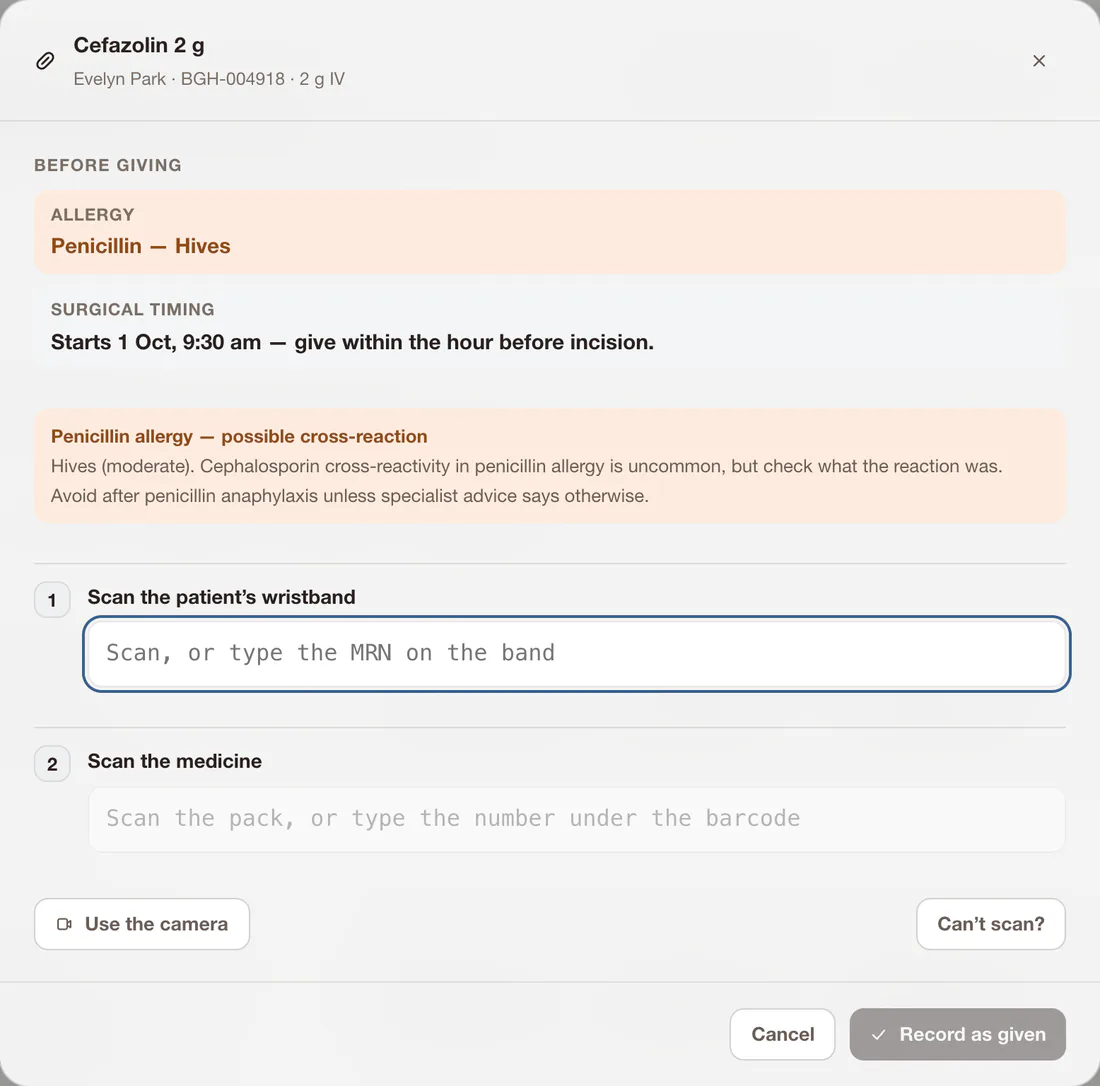
The round is a worklist of what is due. Before a dose is given, the allergy and any cross-reaction are on the screen; then the wristband is scanned, then the pack.
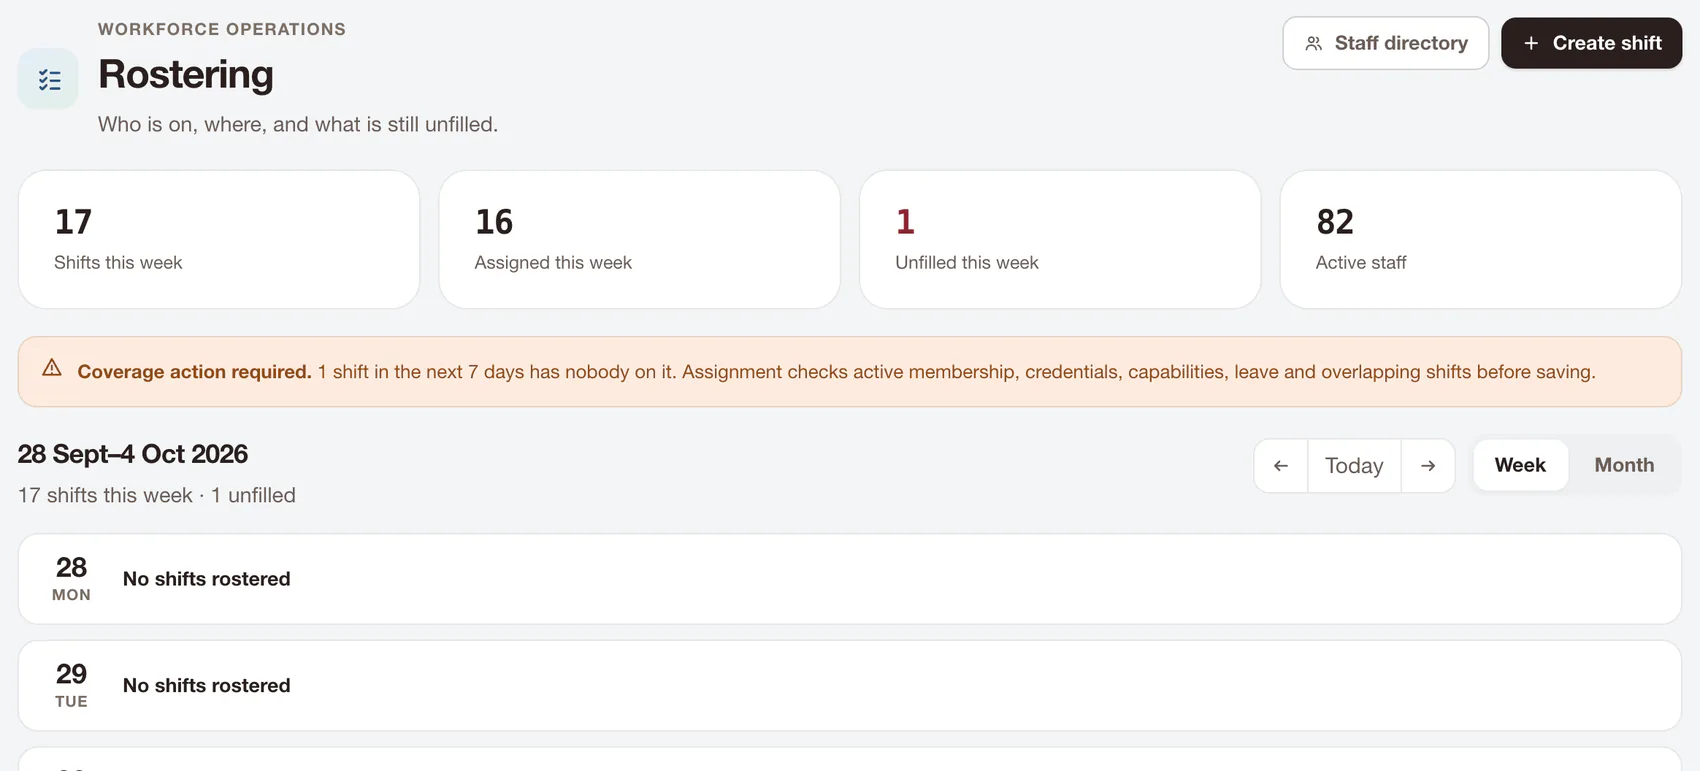
Coverage is planned week by week or month by month, using the same calendar the clinic uses for appointments. Moving a shift is a first-class action, not a delete and re-create.
Product screens from the Lunas demo, with invented patients and staff.
The same controls that make the clinical record defensible apply to every operational transition.
Every record belongs to one organisation. A request from another organisation cannot read it and cannot change it — it is answered as though the record does not exist, so nothing leaks by its absence.
Each module names the roles that may write to it. A clinician, a nurse and an administrator see different actions on the same record, and the check runs on the server rather than in the interface.
Status changes, notes, roster moves and submissions are written to a sequenced audit chain as they happen, recording the actor, the resource and what changed.
Preview workflows still require site configuration, validation and clinical-governance approval before live use.
Lunas Edge puts Lunas on a tower server on site, so the wards keep working when the connection doesn’t and catch up with the cloud when it’s back. Lunas Edge AI keeps consultation audio in the building.
Hospital deployments start with the modules you actually run, the roles that use them and the reporting you are accountable for. Tell us the shape of the site and we will map it. We onboard each organisation directly, with the privacy, hosting and governance controls agreed before any real record is entered.